
Far Infrared, Heat Exposure, and Traumatic Brain Injury
An Absent Direct Evidence Base, Adjacent Preclinical Findings, and Heat-Specific Cautions After Brain Injury
Overview
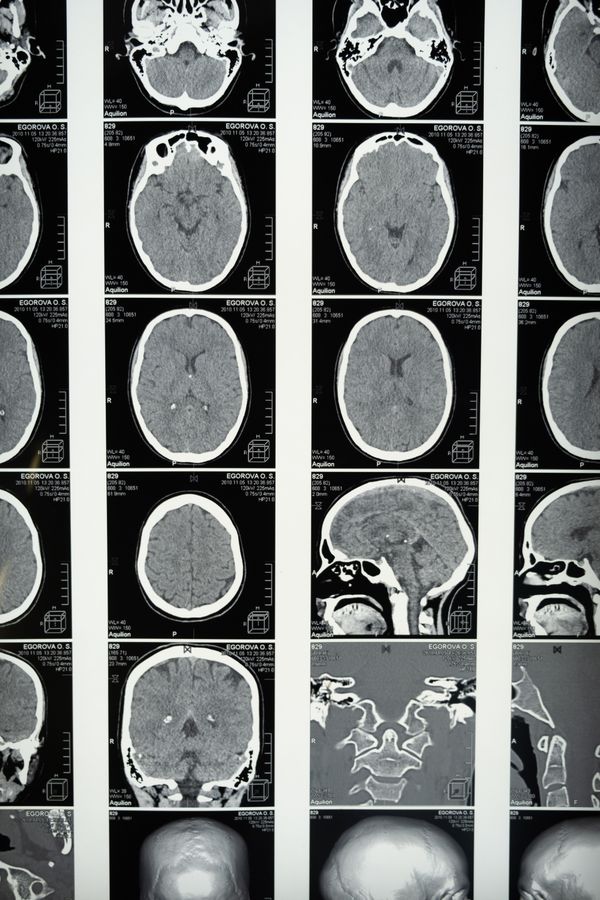
We did not identify a controlled trial of far infrared (FIR) sauna or FIR-emitting devices in traumatic brain injury (TBI) or concussion, and in the searches conducted for this review we did not identify a FIR-specific study in an animal model of TBI.
The nearest FIR-specific preclinical work is in other forms of brain injury and disease (rodent ischemic stroke; transgenic Alzheimer's mice). The human infrared literature in TBI consists of small uncontrolled reports of transcranial red/near-infrared LED treatment, a different band, delivery route, and mechanism.
Because TBI also carries well-documented thermoregulatory and autonomic concerns, and because fever and hyperthermia in the acute phase are associated with worse outcomes, this review emphasizes heat-specific cautions over efficacy.
Absence of identified studies reflects the searches conducted here, not a systematic review.
Human Evidence
No human trial of FIR sauna or FIR devices in TBI or post-concussion syndrome was identified.
Human infrared work in TBI is limited to uncontrolled reports of transcranial light-emitting diode (LED) treatment with red and near-infrared wavelengths in chronic traumatic brain injury, including two case reports and an open-protocol study in chronic mild TBI that report cognitive improvement ( titles as listed in ClinicalTrials.gov NCT02582593 ).
These lack control groups, use scalp-applied non-thermal light, and do not bear on FIR sauna. No effect size from them is reported here.
Adjacent Preclinical Evidence — Other Brain Injury and Disease Models
Ischemic Stroke (Rat MCAO)
In middle cerebral artery occlusion rats, daily 30-minute FIR irradiation reduced infarct volume, alleviated cerebral edema, and improved neurological function; proteomic analysis identified upregulation of eight proteins including the mitochondrial fusion regulator optic atrophy 1 (OPA1), and OPA1 knockdown partly abolished the protective effects (Neural Regen Res, doi:10.4103/NRR.NRR-D-25-00399).
Ischemic stroke is a distinct injury mechanism from impact-induced TBI; the relevance is that mitochondrial dysfunction, oxidative stress, and neuroinflammation are also described as features of the TBI secondary injury cascade.
Alzheimer's Disease Mouse Models
FIR-specific studies in three transgenic AD models reported two positive cognitive outcomes (Li 2022, J Neuroinflammation; a 2025 TgCRND8 study, Neuromolecular Medicine) and one null cognitive result despite favorable neurotrophic factor changes (Fukui 2021, PLOS ONE 16(6):e0253320); see the companion Alzheimer's review.
These models of progressive amyloid pathology do not reproduce traumatic injury, and the mixed cognitive results caution against assuming a general neuroprotective effect.
A Note on Terminology
“Far infrared” is not defined uniformly in this literature: the International Commission on Illumination divides infrared into near (0.7–1.4 µm), middle (1.4–3 µm), and far (3–1000 µm); some papers define far infrared as 15 µm–1 mm; and the studies above used different emitters (for example, 3–25 µm in Li 2022). Comparisons across studies and to a specific device's 4–14 µm output should account for this.
Separately, “near-infrared” appears in TBI research as an imaging or monitoring modality (for example, near-infrared imaging of glymphatic clearance in a rat repetitive-injury model); those are measurement tools, not therapies.
Heat Physiology After TBI
Fever and Hyperthermia in the Acute Phase
Fever in the acute phase after TBI has been associated with neurological severity, worsened functional outcomes, increased intracranial pressure, lower Glasgow Coma Scale scores, and longer ICU stays, and a rodent study of repetitive concussion found that mild hyperthermia aggravated glucose metabolic consequences, with the authors highlighting temperature management in the acute period (PMC7013838).
That paper also cites work reporting that neuropathological damage was exacerbated when the brain was hyperthermic (39°C) directly before a mild injury.
This evidence concerns fever and brain hyperthermia, largely in severe injury and rodent models, not sauna exposure, and should not be extrapolated beyond the principle that elevated brain temperature in the acute window is a recognized secondary-injury concern.
Autonomic and Thermoregulatory Dysfunction
Autonomic dysfunction is described as a major factor in TBI symptomatology, including mild TBI, and as correlating with morbidity and mortality in moderate and severe TBI (Brain Sci 2017;7:100).
Thermoregulatory impairment, including paroxysmal sympathetic hyperactivity with fever, hypertension, and tachycardia, is recognized after severe brain injury, and the hypothalamic preoptic area contains heat-sensitive neurons (Medscape, Post Head Injury Autonomic Complications).
In adults with persisting post-concussive symptoms, exercise intolerance, defined as exacerbation or reappearance of symptoms during exercise, was present in 81% of 100 patients on a treadmill test (PMC12604302), and altered autonomic cardiovascular function has been examined in this population (PMC12159307).
The pathophysiology of exercise intolerance is poorly understood. We did not identify a study of heat tolerance in post-concussive exercise intolerance or of sauna exposure after TBI.
Mechanistic Rationale — Transferred, Not Direct
A hypothesis for FIR in TBI would draw on FIR-associated cytoprotective and anti-inflammatory signaling (heme oxygenase-1 and Nrf-2 pathway findings in cell culture and AD mouse models) and mitochondrial effects (OPA1 in the rat stroke model) as counters to TBI's neuroinflammation, oxidative stress, and cellular energy crisis.
No study has tested this in TBI, and no human study has shown FIR effects on brain tissue or cerebral perfusion after injury.
Correcting Circulating Claims — Practitioner Advisory
What Patients May Bring
- Wellness and vendor content presenting infrared sauna or infrared devices as supporting brain recovery. We identified no TBI-specific FIR or infrared-sauna trial behind such statements.
- Red/near-infrared transcranial LED reports in chronic TBI cited as support for far-infrared products. Wavelength, delivery, heat, and study design (uncontrolled case reports and an open-protocol study) all differ.
- Generalized “brain” claims drawn from the Alzheimer's mouse literature, which is itself mixed on cognition.
Safety Considerations
Clinical Cautions
- Recent injury or active treatment: heat exposure should not be introduced without clearance from the treating team. Fever and hyperthermia in the acute phase are associated with worse outcomes, and no data support sauna use in the subacute period.
- Symptom provocation: patients whose symptoms are provoked by heat, hot environments, or exertion should treat this as clinically meaningful; a graded, symptom-monitored approach is appropriate and uniform tolerance should not be assumed.
- Seizure risk: patients with post-traumatic seizures or epilepsy should consult their neurologist. A wIRA whole-body hyperthermia trial protocol lists epilepsy among its hyperthermia contraindications (NCT06204458), a trial-design signal, not a TBI finding.
- Post-traumatic headache: headache was the most common adverse event in a randomized trial of strong whole-body hyperthermia (core temperature 38.5°C) in depression, reported by 13 of 15 participants in the heated arm (Mason 2025, NCT05708976). That is a different population and a much higher heat dose than conventional FIR sauna sessions, but is relevant to patients with post-traumatic headache.
- Balance, dizziness, judgment, and self-monitoring may be impaired; supervision for entry, seating, and exit is advisable.
- Medications used after TBI may affect sweating, blood pressure, or alertness; review before heat exposure.
- Cardiovascular, conduction, and autonomic considerations in companion reviews in this series (cardiovascular, conduction disease, Parkinson's, HPA axis/autonomic) may apply in individual patients.
- No claim in this document should be represented to patients as evidence that FIR treats, accelerates recovery from, or prevents complications of TBI or concussion.
Evidence Grading Summary
| Domain | Model / Modality | Finding | Tier |
|---|---|---|---|
| FIR sauna / FIR devices, human TBI or concussion | N/A | No trial identified | Absent |
| FIR, animal TBI models | N/A | None identified in searches conducted | Absent (search-limited) |
| FIR, rat ischemic stroke (MCAO) | 30 min daily FIR; OPA1 mitochondrial fusion | Reduced infarct volume and edema; improved neurological function | Positive Preclinical, Different Injury |
| FIR, Alzheimer's mouse models (3 studies) | APP/PS1, 5xFAD, TgCRND8 | Two positive cognitive outcomes, one null | Mixed Preclinical, Different Disease |
| Transcranial red/near-infrared LED, human chronic mTBI | Case reports; open-protocol study | Cognitive improvement reported; no control group | Uncontrolled, Different Modality |
| Acute-phase fever or hyperthermia and TBI outcome | Clinical association; rodent concussion model | Worse outcomes and metabolic effects | Recognized Concern (Not Sauna-Specific) |
| Autonomic dysfunction and exercise intolerance after mTBI | Observational studies | Described; heat tolerance not studied | Recognized Concern, Limited Data |
On smaller screens, swipe horizontally to view the full table.
Clinical Positioning
FIR sauna and FIR-emitting devices should not be presented as a treatment for TBI or concussion, nor as supported by the near-infrared LED literature or by Alzheimer's and stroke models.
For patients who ask, the most useful content is practical: confirm that the injury is not recent and symptoms are stable, obtain clearance from the treating team, screen for seizures and medication effects, and use a graded, supervised, symptom-monitored approach framed as a comfort choice within existing rehabilitation care.
References
Far-infrared irradiation restores mitochondrial dynamics to ameliorate ischemic stroke. Neural Regen Res. doi:10.4103/NRR.NRR-D-25-00399. PMC13568656.
Li Q, et al. Far infrared light irradiation enhances Aβ clearance via increased exocytotic microglial ATP and ameliorates cognitive deficit in Alzheimer's disease-like mice. J Neuroinflammation 2022. doi:10.1186/s12974-022-02521-y.
Fukui K, Kimura S, Kato Y, Kohno M. Effects of far infrared light on Alzheimer's disease-transgenic mice. PLOS ONE 2021;16(6):e0253320.
Far-Infrared Radiation Ameliorates the Cognitive Dysfunction in an Alzheimer's Disease Transgenic Mouse via Modulating Jak-2/Stat3 and Nrf-2/HO-1 Pathways. Neuromolecular Med 2025. doi:10.1007/s12017-025-08860-2.
Improved cognitive function after transcranial, light-emitting diode treatments in chronic, traumatic brain injury: two case reports; and Significant improvements in cognitive performance post-transcranial, red/near-infrared light-emitting diode treatments in chronic, mild traumatic brain injury: open-protocol study. As listed in the reference list of ClinicalTrials.gov NCT02582593.
Mild Hyperthermia Aggravates Glucose Metabolic Consequences in Repetitive Concussion. PMC7013838.
Autonomic Dysfunction after Mild Traumatic Brain Injury. Brain Sci 2017;7:100. PMC5575620.
Altered autonomic cardiovascular function in adults with persisting post-concussive symptoms and exercise intolerance. PMC12159307.
Exploring exercise intolerance in adult patients with persistent post-concussion symptoms after mild traumatic brain injury. PMC12604302.
Post Head Injury Autonomic Complications: Background, Etiology and Pathophysiology, Epidemiology. Medscape ( emedicine.medscape.com/article/325994).
Mason AE, Hartogensis W, Chowdhary A, et al. A Randomized Trial Testing a Novel Mind and Body Intervention for Depression: CBT and WBH. Glob Adv Integr Med Health 2025;14:27536130251387714. NCT05708976.
Evaluation of the Efficacy of Mild Water-filtered Infrared-A Whole-body Hyperthermia in Patients With Post-COVID Syndrome (HyPoCo). ClinicalTrials.gov NCT06204458.


















